


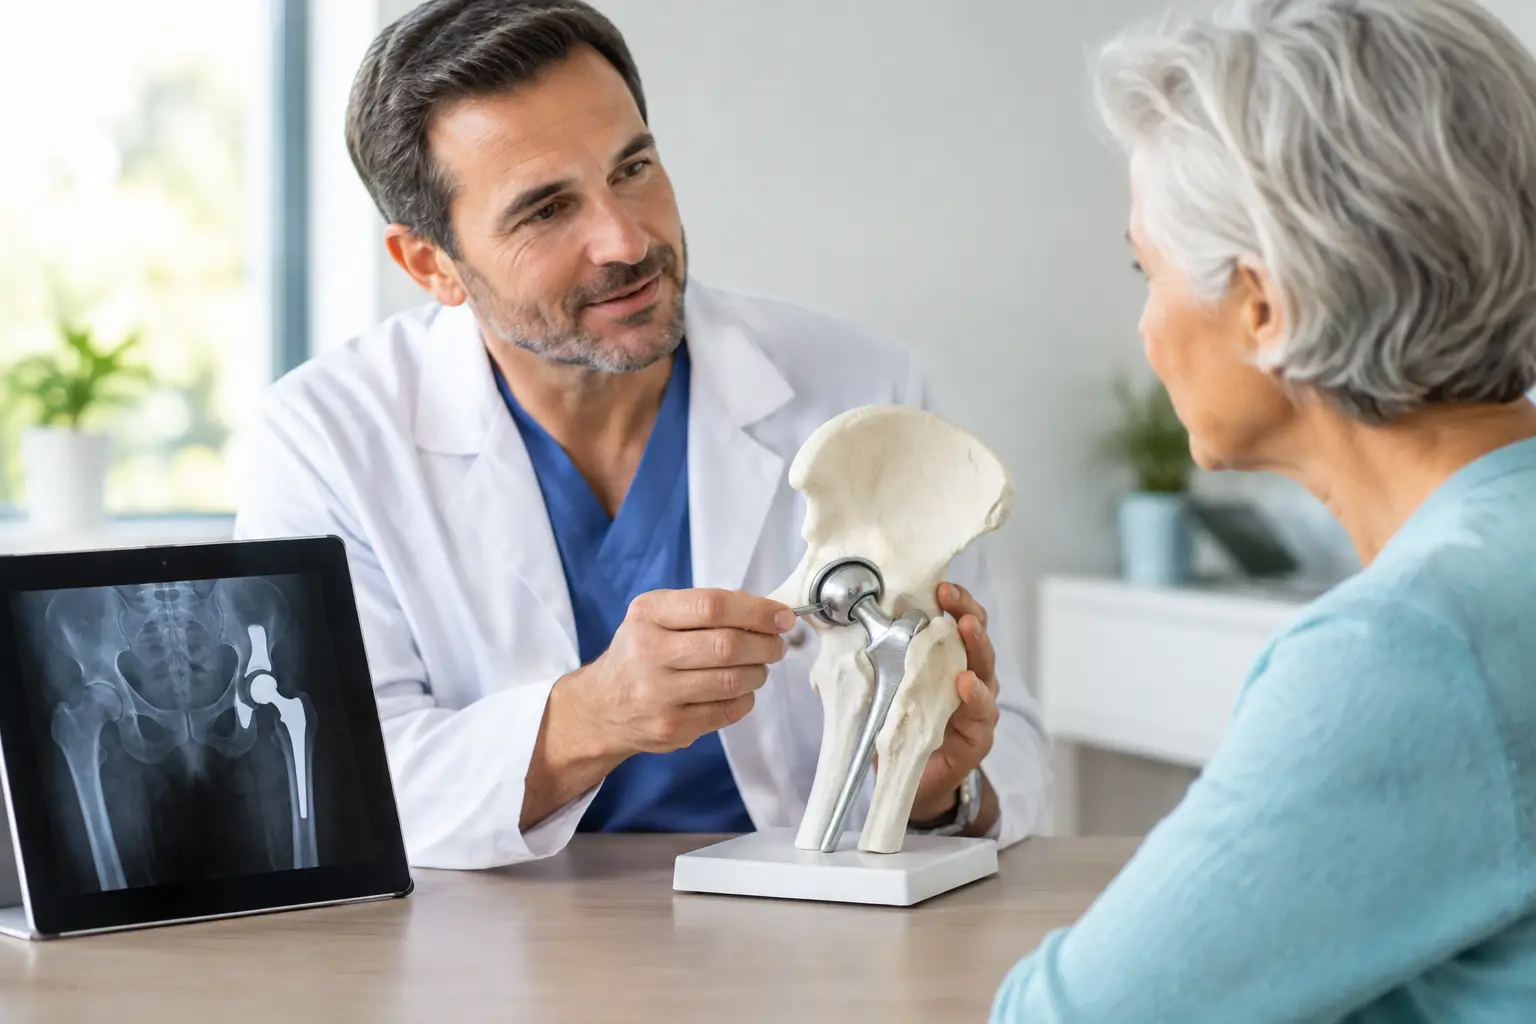
Hip pain can gradually make a once-ordinary day feel carefully negotiated: getting out of the car, climbing stairs, putting on shoes or sleeping comfortably. For people whose pain and stiffness are no longer responding to sensible non-operative treatment, a total hip replacement can be a reliable way to reduce pain, restore movement and return to the activities that give life its shape.
It is, however, a significant operation rather than a decision to rush. The right time for surgery is not determined by an X-ray alone. It comes from understanding how the hip is affecting your daily life, what treatments you have already tried, your general health and what you hope to achieve.
What does total hip replacement involve?
A total hip replacement, also called total hip arthroplasty, replaces the damaged surfaces of the ball-and-socket hip joint with carefully selected artificial components. The worn ball at the top of the thigh bone is replaced with a metal or ceramic ball on a stem, while the damaged socket is resurfaced with a durable cup and liner.
The aim is not simply to produce a better-looking X-ray. It is to create a stable, smoothly moving joint that allows you to walk with less pain and greater confidence. Modern implants are designed for long-term use, but no replacement is indestructible. Implant choice, surgical technique and rehabilitation are therefore tailored to the individual rather than treated as a standard package.
Most hip replacements are performed because of osteoarthritis, where the cartilage that cushions the joint has worn away. Other reasons include inflammatory arthritis, damage to the hip following injury, avascular necrosis, or the effects of childhood hip conditions and previous surgery. In some cases, deformity, bone loss or a failed existing replacement makes the operation more complex and demands particularly detailed planning.
When is a hip replacement worth considering?
Pain severity matters, but the pattern and consequences of pain matter just as much. Surgery may be worth discussing when hip symptoms are persistently limiting walking, work, sleep, exercise or independence despite appropriate treatment. Some people reach that point because they can no longer manage a daily walk; others because pain prevents them from caring for family, travelling or enjoying sport.
Before recommending surgery, a specialist will usually consider your symptoms alongside examination findings and imaging. X-rays remain central for assessing arthritis and joint shape, while further scans may be helpful in selected complex cases. The important question is whether the findings explain the symptoms and whether replacing the joint is likely to make a meaningful difference.
Non-operative measures are often appropriate first steps, particularly when symptoms are intermittent or manageable. These may include activity modification, physiotherapy, weight management where relevant, pain relief, and targeted injections in selected circumstances. They can reduce symptoms and help preserve function, but they do not reverse advanced joint arthritis. If these options no longer provide sufficient relief, repeatedly postponing a well-indicated operation can mean spending more time in avoidable pain and losing strength before recovery begins.
There is no universal age at which a total hip replacement becomes appropriate. A fit, active person in their fifties with severe, life-limiting arthritis may be a better candidate than someone older whose symptoms remain tolerable. Equally, younger patients need an honest discussion about activity expectations and the possibility that an implant may eventually require revision later in life.
Planning the operation around your hip and your life
Good outcomes begin before the day of surgery. Careful pre-operative planning considers leg length, hip anatomy, bone quality, previous operations and the type of implant most suitable for you. In straightforward cases, established implant designs provide excellent results. Where anatomy is unusual, there has been previous trauma or surgery, or bone loss is present, more specialised planning and custom options may be considered.
Your wider health is also part of the decision. Conditions such as diabetes, heart or lung disease, anaemia and osteoporosis may need optimisation beforehand. Smoking can affect wound healing and infection risk, so stopping before surgery is strongly advised. This preparation is not an administrative hurdle: it is a practical way of making surgery and recovery safer.
A clear consultation should also cover the approach to surgery, anticipated hospital stay, pain control, blood-clot prevention and the support available after discharge. Ask what restrictions, if any, will apply in the early weeks and when you can reasonably expect to resume driving, work and particular forms of exercise. The answers depend on your work demands, home set-up, recovery progress and the nature of the operation.
Recovery after total hip replacement
Most patients stand and begin walking with physiotherapy soon after surgery, usually using crutches or walking sticks initially. The early focus is safe mobility: getting in and out of bed, managing stairs where necessary, and learning the exercises that build movement and strength.
Recovery is progressive rather than instant. The surgical pain settles over the first weeks, but tiredness, muscle weakness and swelling are common while the body heals. Many people move from crutches to a stick and then unaided walking as control and comfort improve. The precise pace varies. A person with good pre-operative strength and a straightforward procedure may progress quickly, while someone with longstanding stiffness, complex anatomy or other health conditions may need more time.
Driving is usually considered once you can safely control the vehicle and perform an emergency stop, without relying on strong pain medication. Returning to desk-based work may be possible within several weeks for some patients, whereas physically demanding roles often require longer. Low-impact activities such as walking, swimming, cycling and golf are commonly realistic goals once recovery is established. High-impact running, jumping and contact sports require an individual discussion because repeated heavy loading may affect the longevity of the implant.
Physiotherapy and regular movement are central to the result. The operation addresses the damaged joint surfaces, but rebuilding confidence, balance and muscle strength takes consistent work. It is also sensible to prepare the home in advance: arrange help if needed, keep essentials within easy reach, remove trip hazards and plan meals for the first few days.
Understanding the benefits and risks
For appropriately selected patients, total hip replacement has a strong record of improving pain and function. Many people describe the benefit not as a dramatic athletic achievement, but as the return of normal freedoms: walking without planning every route, sleeping through the night, taking a holiday, or keeping pace with grandchildren.
Every operation carries risk, and an informed decision should make room for that reality. Important risks include infection, blood clots, bleeding, dislocation, nerve or blood-vessel injury, fracture, leg-length difference, persistent pain and implant loosening or wear over time. These complications are uncommon, but they are taken seriously because they can require further treatment or, occasionally, revision surgery.
Risk is not identical for every patient. Previous hip surgery, obesity, smoking, certain medical conditions and complex bone anatomy can alter the picture. This is why specialist assessment and candid discussion are essential. The goal is not to promise a perfect hip, but to balance the likely benefits against the risks in your own circumstances.
Questions that help you make a confident decision
A consultation is your opportunity to understand both the operation and the thinking behind it. It is reasonable to ask whether surgery is the best option now, what alternatives remain, what implant and surgical plan are proposed, and what outcome is realistic for your preferred activities. You may also want to ask how your individual health factors affect recovery and what support will be available if progress is slower than expected.
For patients in London and Kent, seeing a fellowship-trained hip specialist can be particularly valuable where symptoms are complex, previous surgery has failed, or there is uncertainty about whether replacement is necessary. Precision in planning matters, but so does being listened to. You should leave a consultation with a clear understanding of your options, not pressure to proceed.
Choosing total hip replacement is ultimately about more than replacing a joint. It is about deciding whether the likely improvement in comfort and mobility justifies surgery at this point in your life. When that decision is made with careful assessment, honest advice and a recovery plan built around your goals, it can be the start of returning to the everyday movement you have been missing.