


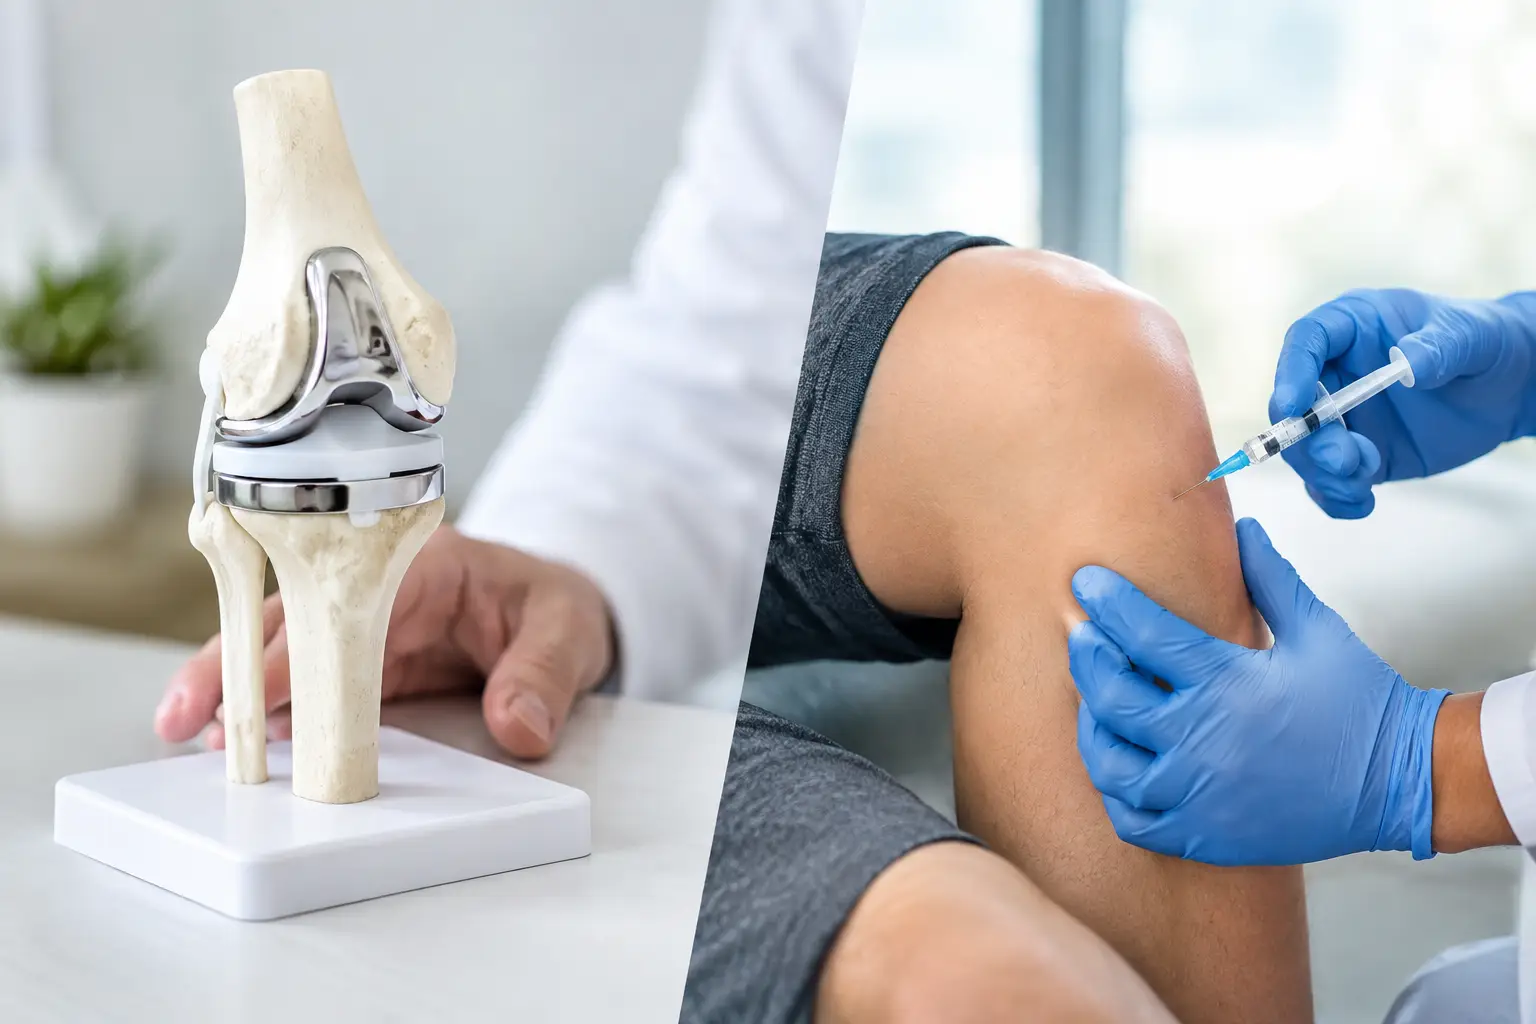
When knee pain starts dictating how far you can walk, whether you use the stairs or whether you can keep up with family life, the choice can feel urgent. Yet knee replacement versus injections is rarely a simple choice between a major operation and a quick fix. The right treatment depends on what is causing the pain, how advanced the joint damage is, what you have already tried, and what you need your knee to do.
For some people, an injection creates a valuable window of reduced pain that makes exercise, work or an important event more manageable. For others, repeated injections only postpone a treatment that is more likely to provide lasting relief. A careful specialist assessment helps put that decision in context.
What injections can and cannot do
Knee injections are non-operative treatments used to reduce symptoms or, in some cases, improve the joint environment. They do not replace worn cartilage, correct significant deformity or reverse established arthritis. Their role is to help selected patients manage pain and maintain movement while a longer-term plan is considered.
A steroid injection can reduce inflammation within the joint and may be particularly helpful when a knee is swollen, irritated or flaring. Relief can be substantial, but it is variable and usually temporary. Some patients benefit for weeks or months; others notice little change. Steroid injections are generally used thoughtfully rather than repeatedly without a clear reason, as frequent injections are not an effective long-term answer for a severely arthritic knee.
Hyaluronic acid injections aim to improve lubrication within the joint. Results vary, and they tend to be more useful for some people with mild to moderate osteoarthritis than for those with advanced bone-on-bone arthritis. Platelet-rich plasma, or PRP, uses a concentration of platelets from your own blood and may be considered in certain cases. Arthrosamid is another non-operative option that may be appropriate for selected patients with knee osteoarthritis.
The most useful injection is not necessarily the newest one. It is the treatment that fits the diagnosis, your medical history and your goals, with a realistic understanding of how long any benefit may last.
When injections are a sensible first step
An injection can be a reasonable option when symptoms are troublesome but the knee joint is not yet severely damaged, or when pain appears to be driven by inflammation. It can also help someone engage more effectively with physiotherapy and muscle strengthening. Stronger thigh muscles, improved balance and better movement patterns can reduce load through the knee and improve confidence in daily activities.
Injections may also be appropriate if you need to delay surgery for a practical or medical reason. Perhaps you are caring for someone, planning a significant trip, recovering from another illness or working towards a healthier weight before an operation. In these situations, symptom relief can be useful, provided it is part of a clear plan rather than an indefinite cycle.
An injection may be less likely to help when X-rays show advanced arthritis and the main problem is mechanical pain from a badly worn joint. Pain at rest or at night, increasing bow-legged or knock-kneed alignment, and a steadily shrinking walking distance can all indicate that the condition has moved beyond what injections can reliably address.
Knee replacement versus injections: the key difference
The central difference is the purpose of treatment. Injections aim to manage symptoms for a period of time. Knee replacement addresses the damaged joint surfaces themselves by replacing them with carefully positioned implants designed to restore alignment, reduce pain and improve function.
A total knee replacement is usually considered when arthritis affects more than one area of the knee and symptoms remain significant despite appropriate non-operative treatment. A partial knee replacement may be suitable when wear is confined to one compartment of the knee and the ligaments, alignment and other parts of the joint meet specific criteria. Not every painful knee needs a replacement, but neither should someone continue struggling simply because they feel surgery is a last resort.
Replacement surgery is a substantial commitment. It involves an operation, a period of rehabilitation and patience while strength and confidence return. The early weeks can be demanding, particularly with sleep, swelling and regaining knee bend. However, for the right patient with advanced arthritis, it offers a more durable route to less pain and better mobility than repeated short-term treatments.
Signs it may be time to discuss surgery
There is no single X-ray result or birthday that determines when knee replacement is appropriate. The timing is personal, but it should be based on the combined effect of symptoms, examination findings and imaging rather than any one factor alone.
It is sensible to seek a surgical opinion if pain is regularly disturbing sleep, walking has become increasingly limited, or you are avoiding work, exercise and social plans because of your knee. Difficulty with everyday tasks such as getting out of a chair, shopping or managing stairs matters just as much as a scan result. So does the extent to which pain medication and injections are no longer providing meaningful relief.
Some people wait until they can barely move before asking about surgery. That is understandable, but it is not always necessary or beneficial. Maintaining reasonable strength and mobility before an operation can support rehabilitation afterwards. The aim is not to operate too early, but to avoid allowing pain and loss of function to take over your life unnecessarily.
The trade-offs to consider honestly
Injections have the advantage of being less invasive, requiring little recovery time and carrying fewer immediate risks than surgery. They may help you remain active while symptoms are still manageable. Their limitation is uncertainty: the degree and duration of relief cannot be guaranteed, and the underlying arthritis remains.
Knee replacement has a longer recovery and small but important surgical risks, including infection, blood clots, stiffness and ongoing pain. It also requires active participation in rehabilitation. Most people considering surgery want to know when they will be “back to normal”, but recovery is individual. Progress is usually measured in months, not days, and the target is a comfortable, reliable knee for everyday life rather than a return to every high-impact activity.
The benefits can be considerable when surgery is well indicated and carefully planned. Many patients are able to walk further, sleep better, travel, work and return to the hobbies that pain had gradually taken away. A specialist should discuss both the likely gains and the limitations in terms that relate to your own priorities.
Why diagnosis and planning matter
Not all knee pain is caused by arthritis. Meniscal injury, ligament problems, kneecap joint arthritis, referred pain from the hip and previous surgery can each alter the recommended treatment. This is why treatment should not be chosen from an X-ray report alone or because a friend had a particular injection or operation.
A thorough consultation considers where the pain is, when it occurs, the pattern of swelling, your range of movement, leg alignment, previous treatments and general health. Imaging is then interpreted alongside the clinical examination. If surgery is appropriate, detailed planning helps determine whether a total or partial replacement is suitable and how to restore the knee’s alignment as accurately as possible.
For patients who have had previous knee surgery or an unsuccessful joint replacement, the decision can be more complex. A revision or reconstructive opinion should identify the specific source of the problem before any further treatment is proposed.
Making a decision around your life
The question is not whether injections or replacement is universally better. It is whether the proposed treatment gives you a credible path towards less pain, safer movement and the activities that matter to you. A good consultation should leave you clear about the diagnosis, the alternatives, the expected recovery and what may happen if you wait.
Mr Kam Cheema’s specialist hip and knee practice takes this approach: honest advice first, followed by a treatment plan that reflects the condition of the joint and the life you want to return to. Whether an injection is the right next step or knee replacement offers the more durable answer, the decision deserves time, precision and a plan you can feel confident following.